Erythema chronicum migrans
Begutachtet von Dr Doug McKechnie, MRCGPZuletzt aktualisiert von Dr Colin Tidy, MRCGPZuletzt aktualisiert 12. Juni 2023
Erfüllt die redaktionelle Richtlinien
- HerunterladenHerunterladen
- Teilen
- Language
- Diskussion
- Audio-Version
- Zu bevorzugten Quellen bei Google hinzufügen
Medizinische Fachkräfte
Fachartikel sind für die Nutzung durch Gesundheitsfachkräfte konzipiert. Sie werden von britischen Ärzten verfasst und basieren auf Forschungsergebnissen, britischen und europäischen Richtlinien. Möglicherweise finden Sie einen unserer Gesundheitsartikel nützlicher.
What is erythema chronicum migrans?
Erythema chronicum migrans is a characteristic clinical feature of Lyme disease (Lyme borreliosis). It is a distinctive rash, which occurs in the majority of people infected with Borrelia burgdorferi. This infection is transmitted to humans by the bite of a tick from the genus Ixodes.
How common is erythema chronicum migrans? (Epidemiology)1
Lyme disease is not common in the UK, with an estimated 2,000 to 3,000 new cases each year in England and Wales.
In the UK, areas where infection is acquired include Exmoor, the New Forest, the South Downs, parts of Wiltshire and Berkshire, Surrey, West Sussex, Thetford Forest, the Lake District, the North Yorkshire moors and the Scottish Highlands.
Infection may also be acquired abroad and mostly by holidaymakers. The majority are acquired in the USA, France, Germany, Scandinavia and other northern, eastern and central European countries. The infection can also be found in temperate forested areas of Asia, including Russia, China and Japan.
In Europe erythema chronicum migrans occurs as a presenting feature in up to 90% of those infected.2 Presentation does appear to depend upon the Borrelia species involved; therefore, in other parts of the world the rash may be a less common presenting sign.
Symptoms of erythema chronicum migrans (presentation)3
The characteristic manifestation of early Lyme disease (stage 1) is erythema chronicum migrans: a circular rash at the site of the infectious tick attachment, which radiates from the bite. It can appear within 3-36 days, but typically in 7-10.
It starts as a red macule or papule at the site of the tick bite after a (typically 7- to 10-day) delay.
The rash is round or oval, and pink, red or purple. There is often central sparing giving a target-like appearance, and the diameter is usually larger than 5 cm. The nature of the rash and the likelihood of its presence are partly dependent on the species involved and therefore differ between continents.
Erythema migrans 'Zielscheiben'-Ausschlag der Lyme-Borreliose
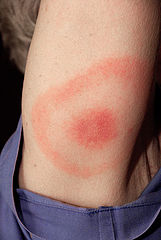
Untreated, this can last for some weeks, but eventually resolves.
Common areas include the popliteal fossa, groin, the axilla, the thorax and the trunk. The hairline and scalp are especially common in children.
It may be associated with other symptoms of infection, including fatigue, myalgia, arthralgia, headache, fever, stiff neck, and regional lymphadenopathy.
It may also be associated with later developments such as carditis, neurological disease, arthritis, and acrodermatitis chronica atrophicans (a swollen, bluish-red skin lesion on a distal extremity).
The National Institute for Health and Care Excellence (NICE) recommends diagnosing Lyme disease in people with erythema migrans that:4
Increases in size and may sometimes have a central clearing.
Is not usually itchy, hot or painful.
Usually becomes visible from 1 to 4 weeks (but can appear from 3 days to 3 months) after a tick bite and lasts for several weeks.
Is usually at the site of a tick bite.
In the absence of erythema migrans, the diagnosis of Lyme disease can be very difficult with non-specific clinical signs and symptoms that may or may not be supported by laboratory evidence.5
Differentialdiagnose6
Local tick bite reactions.
Untersuchungen1 3
For anyone with erythema migrans who have no evidence of focal symptoms of Lyme disease (eg neurological, cardiac, or joint involvement), investigations are not required and start treatment with oral antibiotics (see below).
Management of erythema chronicum migrans4 7
Although the rash will resolve spontaneously over weeks or months, antibiotics help prevent progression to disseminated Lyme disease.
For the treatment of Lyme disease without focal symptoms (eg, neurological, carditis) but with erythema migrans and/or non-focal symptoms, NICE recommends:
First choice: oral doxycycline: 100 mg twice per day or 200 mg once per day for 21 days.
First alternative: oral amoxicillin: 1 g 3 times per day for 21 days.
Second alternative: oral azithromycin: 500 mg daily for 17 days (azithromycin should not be used to treat people with cardiac abnormalities associated with Lyme disease because of its effect on QT interval).
Prevention of erythema chronicum migrans
Avoid exposure to tick bites.
Remove ticks as soon as possible. Ticks take some time to transmit infection, so this may be prevented if removed quickly.
Antibiotic prophylaxis can be offered in endemic areas under certain circumstances if the tick bite can be positively identified.
Exklusive Updates für medizinisches Fachpersonal
Bleiben Sie informiert mit den neuesten klinischen Updates, professionellen Einblicken und evidenzbasierten Leitlinien. Der Patient Pro-Newsletter stellt wesentliche Inhalte für Gesundheitsfachkräfte zusammen – direkt in Ihren Posteingang geliefert.
Durch das Abonnieren akzeptieren Sie unsere Datenschutzrichtlinie. Sie können sich jederzeit abmelden. Wir verkaufen Ihre Daten niemals.
Weiterführende Lektüre und Referenzen
- Mygland A, Ljostad U, Fingerle V, et al; EFNS guidelines on the diagnosis and management of European Lyme neuroborreliosis. Eur J Neurol. 2010 Jan;17(1):8-16, e1-4. doi: 10.1111/j.1468-1331.2009.02862.x. Epub 2009 Nov 23.
- Erythema chronicum migrans; DermIS (Dermatologisches Informationssystem)
- Prevention and control of tick-borne disease in Europe - Information to healthcare professionals; Europäisches Zentrum für die Prävention und die Kontrolle von Krankheiten
- Coburn J, Garcia B, Hu LT, et al; Lyme Disease Pathogenesis. Curr Issues Mol Biol. 2021;42:473-518. doi: 10.21775/cimb.042.473. Epub 2020 Dec 23.
- Lyme disease (and erythema migrans); Primary Care Dermatology Society (PCDS). Last updated May 2022.
- Lyme-Borreliose; DermNet.
- Borreliose: Leitfaden, Daten und Analyse; Public Health England - jetzt UK Health Security Agency (zuletzt aktualisiert 2022)
- The epidemiology, prevention, investigation and treatment of Lyme borreliosis in United Kingdom patients: a position statement by the British Infection Association; J Infect. 2011 May;62(5):329-38. doi: 10.1016/j.jinf.2011.03.006. Epub 2011 Mar 21.
- Lyme-Borreliose; NICE CKS, November 2022 (nur für UK-Zugang)
- Lyme-Borreliose; NICE-Richtlinien (April 2018 - zuletzt aktualisiert Oktober 2018)
- Bobe JR, Jutras BL, Horn EJ, et al; Recent Progress in Lyme Disease and Remaining Challenges. Front Med (Lausanne). 2021 Aug 18;8:666554. doi: 10.3389/fmed.2021.666554. eCollection 2021.
- Shapiro ED; Clinical practice. Lyme disease. N Engl J Med. 2014 May 1;370(18):1724-31. doi: 10.1056/NEJMcp1314325.
- Britisches Nationales Arzneimittelverzeichnis (BNF); NICE Evidenzdienste (nur in Großbritannien zugänglich)
Über den AutorVollständige Biografie anzeigen
Aktualisiert von

Dr Colin Tidy, MRCGP
Allgemeinmediziner, Medizinischer Autor
MBBS, MRCGP, MRCP (Paediatrics), DCH
Dr. Colin Tidy ist ein NHS-Arzt mit Sitz in Oxfordshire.
Über den RezensentenVollständige Biografie anzeigen

Dr Doug McKechnie, MRCGP
Medizinischer Autor
MA, MBBS, MSc, DRCOG, MRCP(UK), MRCGP(2021), FHEA
Dr. Doug McKechnie ist ein NHS-Hausarzt, der in London arbeitet. Er arbeitet klinisch in Vollzeit und ist außerdem stellvertretender Leiter des Moduls für klinische und berufliche Praxis an der University College London Medical School.
Artikelverlauf
Artikel auch verfügbar in Englisch, Deutsch, Spanisch, Französisch, Italienisch, Portugiesisch, Hindi, Hebräisch, Arabisch, und Schwedisch.
Nächste Überprüfung fällig: 12. Mai 2028
12. Juni 2023 | Neueste Version

Fragen, teilen, verbinden.
Durchsuchen Sie Diskussionen, stellen Sie Fragen und teilen Sie Erfahrungen zu Hunderten von Gesundheitsthemen.

Fühlen Sie sich unwohl?
Bewerten Sie Ihre Symptome online kostenlos
Mehr in der Dermatologie
- Albinismus
- Coxsackievirus-Infektion
- Kutaner Filariasis
- Arzneimittelallergie
- Erythema multiforme
- Erythrodermie
- Granuloma annulare
- Lipom
- Bösartiges Melanom der Haut
- Mastozytose und Mastzellenerkrankungen
- Periorale Dermatitis
- Prurigo nodularis
- Rosazea und Rhinophym
- Seborrhoische Warze
- Stevens-Johnson-Syndrom
- Sturge-Weber-Syndrom
- Sonnenbrand
- Systemische Sklerose
- Toxokariasis